

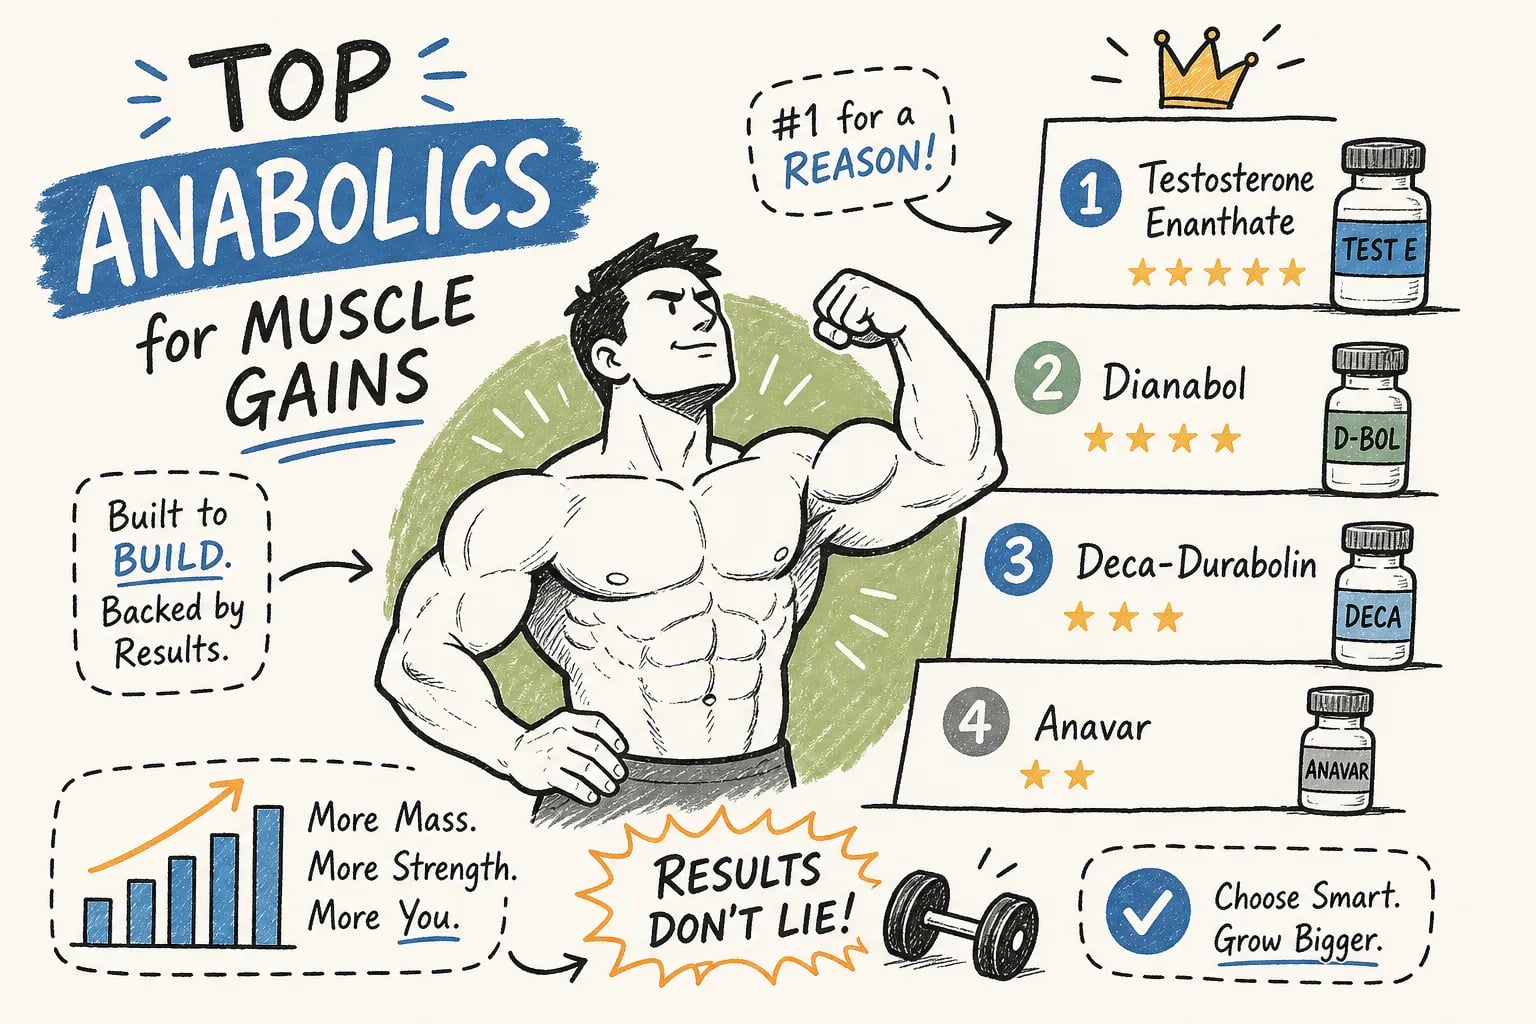
In a landmark controlled trial, men using 600mg per week of testosterone enanthate for ten weeks gained roughly 6kg of lean mass. The group that trained naturally gained about 2kg over the same period. That’s not a small difference. That’s the entire gap between a good year of natural training and ten weeks on a single compound, and the numbers are hard to ignore. So what are the best steroids for building muscle mass fast? That question keeps coming up in every serious bodybuilding conversation, and the answer deserves a ranked, evidence-grounded breakdown rather than another round of gym mythology.
This article ranks the four compounds most associated with rapid lean mass gains, drawing on controlled clinical data and documented usage patterns. The focus is lean mass changes over 8, 20 week cycles, not scale weight inflated by water retention. Dosing discipline, compound selection, and sourcing pharmaceutical-grade products are what separate real results from wasted cycles and unnecessary health exposure.
What the clinical evidence actually shows about steroid-driven muscle gains
The controlled trial benchmark every bodybuilder should know
The Bhasin et al. study remains the cleanest apples-to-apples comparison in the human literature. Four groups, ten weeks: testosterone plus training produced approximately 6kg of lean mass; testosterone alone produced around 3.2kg; placebo plus training produced about 2kg; and placebo alone produced roughly 0.8kg. Supraphysiologic androgens outperformed natural training by roughly three to one, and testosterone without any training still beat training without testosterone.
That last point gets overlooked constantly. The compound did more work than the gym. This sets the baseline for evaluating every muscle-building steroid on this list and explains why serious competitors treat compound selection as the most consequential variable in their planning.
What are the best steroids for building muscle mass fast: understanding the variables
Not all anabolic-androgenic steroids produce the same results on the same timeline. Injectable versus oral delivery, ester length, aromatization rate, and the anabolic-to-androgenic ratio all shape what you see in the mirror over a 10, 16 week window. Faster-acting compounds, such as oral 17α-alkylated agents like methandrostenolone or short-ester injectables like testosterone propionate, tend to show visible results in weeks one through four. Longer esters build steadily across the full cycle. The ranking below uses clinical lean-mass data where available, documented anabolic-to-androgenic ratios, and established usage patterns across bodybuilding communities.
What are the best steroids for building muscle mass fast: top 4 compounds ranked
1. Testosterone enanthate: the most clinically validated mass builder
Testosterone enanthate is the gold standard among muscle-building steroids. The 6kg lean-mass gain in ten weeks at 600mg per week is the highest documented figure in a clean controlled trial design, and no other compound on this list matches that level of evidence. Common bodybuilding dosing runs 300, 600mg per week over 10, 16 week cycles. Higher doses accelerate gains but also accelerate estrogenic and hematologic steroid side effects, so aromatase inhibitor use is common practice at the upper end, though it carries its own side effects and should not be treated as universally appropriate without individual monitoring.
Testosterone also serves as the backbone of most bulking stacks because any anabolic steroid suppresses the HPG axis (hypothalamic, pituitary, gonadal axis), meaning natural testosterone production shuts down during a cycle. Running testosterone as the base compound solves that problem directly while simultaneously driving mass gains. From a harm-reduction standpoint, testosterone-only is the most straightforward first-cycle option: its effects are better-documented than most other performance-enhancing drugs (PEDs), and its post-cycle management is more predictable. That said, it remains a controlled prescription compound carrying real risks that warrant medical oversight.
2. Dianabol (methandrostenolone): fastest oral kickstart
Dianabol is the classic oral mass builder among anabolic steroids for rapid muscle gains. Clinical reviews and community harm-reduction literature consistently cite it among the most potent oral compounds for rapid early-cycle weight gain, with noticeable onset in the first two to four weeks. The typical application is a kickstart at 25, 50mg per day for four to six weeks while a longer ester like testosterone enanthate builds up in the system, covering the slow ramp-up period and producing fast early results. It is worth noting that controlled data do not clearly show Dianabol outperforming high-dose testosterone in head-to-head lean mass trials; its position here reflects observed rapid onset and widespread documented use rather than a direct clinical superiority claim.
The trade-offs are significant. Dianabol is a 17α-alkylated oral compound, which means hepatotoxicity is a documented concern, not a theoretical one. Liver enzymes typically elevate within weeks of starting, and the compound aromatizes heavily, requiring active estrogen management. It is not a standalone compound for longer cycles, and alcohol should be eliminated entirely while running it.
3. Deca-Durabolin (nandrolone decanoate): steady mass with joint benefits
Pooled controlled data on nandrolone decanoate shows an average of approximately 1.59kg of lean soft tissue gained versus placebo, with individual trials reporting up to 2.8kg over twelve months. Slower than testosterone and Dianabol, but community and observational reports consistently describe the gains as denser and lower in water retention at moderate doses, a pattern not yet fully confirmed in controlled head-to-head comparisons. The typical bodybuilding range is 200, 400mg per week, almost always run alongside testosterone to offset nandrolone’s suppressive effect on natural androgen production.
Nandrolone’s 5-alpha reduction produces a weaker androgen than testosterone, meaning lower androgenic steroid side effects at equivalent doses. The joint-lubricating properties are a practical benefit widely reported by users pushing heavy volume. Most harm-reduction guidance recommends keeping the testosterone-to-Deca ratio at least 2:1 to minimize the low-androgen symptoms nandrolone can cause when run without adequate testosterone support.
4. Trenbolone: high potency, limited human trial data
Trenbolone does not convert to estrogen, which makes it appealing for lean mass cycles where water retention is a concern. In bodybuilding practice it is consistently ranked among the most potent muscle-building steroids available. The significant limitation: human clinical trial data are sparse compared to testosterone or nandrolone, so most of the evidence base is observational and anecdotal rather than controlled.
The androgenic profile is aggressive. Acne, night sweats, sleep disruption, and mood effects are widely reported. Its androgenic potency is roughly five times that of testosterone at equivalent doses, a figure derived primarily from receptor-binding and animal data, since robust human dose-response trials are limited. Typical usage runs 200, 400mg per week (acetate or enanthate ester), almost always paired with testosterone to maintain baseline androgen levels. Trenbolone is reserved for intermediate to advanced users who have already completed multiple testosterone-only cycles and understand how their physiology responds to heavily suppressive compounds.
Dosing ranges and stacking basics
How to think about cycle structure for muscle mass gains
These are community and harm-reduction examples, not medically recommended protocols. All doses discussed exceed approved therapeutic ranges and carry legal and health risks that vary by individual. A foundational bulking stack pairs testosterone enanthate at 400, 500mg per week with Dianabol at 30, 40mg per day for weeks one through four as a kickstart. This covers the early window while the ester builds up in the system, then sustains gains across the remainder of the cycle. A second common approach runs testosterone at 400mg per week alongside Deca at 300mg per week over 12, 16 weeks for steadier, less water-heavy results.
Trenbolone is reserved for users who have already run multiple testosterone-only cycles and have a clear picture of how their body handles androgenic suppression. Adding that layer of complexity beforehand compounds risk without improving outcomes, a mistake documented consistently across harm-reduction literature.
Why ester choice matters more than beginners expect
Short esters like acetate and propionate require more frequent injections but allow faster adjustability when side effects appear. Long esters like enanthate and decanoate are more convenient but slower to clear if problems arise. For a first or second mass cycle, long esters are more practical. The added injection frequency of short-ester protocols adds no meaningful benefit at that stage.
Compound-specific risks you need to factor in
Cardiovascular and endocrine risks across the board
All anabolic steroids suppress the HPG axis (hypothalamic, pituitary, gonadal axis) to some degree, shutting down natural testosterone production during a cycle. Recovery post-cycle depends on compound, dose, and duration. Lipid profiles worsen consistently: HDL typically drops and LDL rises. Research on AAS users documents HDL reductions ranging from 20% to 70% in some cohorts, a meaningful increase in cardiovascular strain.
Long-term AAS use is associated with left ventricular hypertrophy and arterial stiffness in observational data. The HAARLEM study found a positive relationship between supraphysiologic dosing and increased left ventricular wall thickness. Short-cycle users face lower cumulative risk than chronic, multi-year users, but the link between repeated HDL suppression and progressive cardiac remodeling is documented well enough to take seriously.
Compound-specific concerns that change the risk calculus
Dianabol’s distinguishing risk is hepatotoxicity: keep cycles to four to six weeks maximum and eliminate alcohol entirely. Trenbolone’s androgenic side effects are disproportionately pronounced, sleep disruption and mood changes are consistent reports across communities, not surprising given its fivefold androgenic potency relative to testosterone. Nandrolone’s progesterone receptor activity can suppress libido, which is why running it without adequate testosterone is a consistent and well-documented mistake. For testosterone, gynecomastia and erythrocytosis are the most common dose-dependent concerns. Managing estrogen and monitoring hematocrit are standard steps, not optional ones.
Why pharmaceutical-grade purity matters when sourcing these compounds
The problem with underdosed and contaminated products
The unregulated nature of this market means a significant share of products sold as anabolic steroids are underdosed, mislabeled, or contaminated. If the compound in your vial is not what the label says, you are taking on full health exposure with none of the expected return. That is the worst-case scenario: risk without result.
HPLC testing is the pharmaceutical standard for verifying compound identity and purity. It works by separating the steroid from related substances on a chromatographic column and quantifying what fraction of the sample is the target compound versus impurities. Pharmaceutical-grade material is generally expected to test at approximately 99% purity or higher by HPLC, with impurities controlled within tight limits. A supplier that provides batch-specific HPLC documentation is doing something most in this market will not.
What to look for in a supplier: the cGMP standard
cGMP (current Good Manufacturing Practice) certification means the manufacturing facility operates under regulated production standards rather than uncontrolled synthesis. The difference shows up in batch-to-batch purity consistency, which directly affects dosing predictability and cycle safety. BodybuildingCycleOnline maintains cGMP manufacturing standards and makes HPLC purity documentation available by batch, a level of transparency that most suppliers in this space do not offer. Before sourcing any compound, request batch-specific purity documentation. If that documentation is unavailable, treat it as a meaningful signal about that supplier’s quality controls.
Evidence-based alternatives and harm-reduction steps
The safer baseline that still moves the needle
Before adding exogenous androgens to the equation, the most common gap is in training consistency, protein intake, and sleep quality. The evidence-backed protein target for lifters is 1.6, 2.2g per kg of bodyweight per day. Creatine monohydrate has the strongest documented risk-to-benefit ratio of any supplement studied for strength and lean mass. Its effect size is real, replicated across dozens of trials, and carries essentially no risk in healthy people. It is not a substitute for anabolic steroids in terms of magnitude, but it is the most defensible starting point for anyone who has not yet optimized the fundamentals.
If you are going to cycle, harm reduction is non-negotiable
Get bloodwork before, during, and after a cycle: lipids, hematocrit, liver enzymes, and a full hormone panel at minimum. Baseline data is the only way to know what a cycle is actually doing to your numbers. Run structured post-cycle therapy with compounds like clomiphene or tamoxifen to support HPG axis recovery. Skipping PCT extends the window of suppressed natural testosterone and compounds long-term endocrine risk. Keep cycles short, doses reasonable, and off-time at least equal to on-time, a harm-reduction heuristic widely cited in community guidelines, though optimal timing should be calibrated to individual health status and ideally supervised by a clinician. The cumulative cardiovascular and endocrine burden of back-to-back cycling is where most of the serious long-term risk accumulates.
Putting it together
If you want to know what are the best steroids for building muscle mass fast, the clinical evidence gives a clear hierarchy. Testosterone enanthate leads on every dimension that matters: evidence quality, dosing predictability, and stackability with other muscle-building steroids. Dianabol provides a fast oral kickstart with well-documented hepatotoxic risk. Deca-Durabolin delivers steadier, joint-friendly gains over longer cycles. Trenbolone offers high potency at a higher androgenic cost and limited human trial data to back it up.
Compound selection matters, but dosing discipline, cycle structure, and sourcing verified pharmaceutical-grade products are equally decisive. The starting question for any sourcing decision is whether batch-specific purity documentation exists. BodybuildingCycleOnline provides that documentation alongside cGMP manufacturing standards, a concrete baseline to evaluate before committing to a supplier.
Bloodwork and medical oversight are not optional in this context. They are what separates a calculated decision from a blind one. The clinical evidence supports the efficacy of these performance-enhancing drugs clearly enough. What it supports just as clearly is that the cardiovascular and endocrine costs are real, measurable, and cumulative. Know your numbers before you start, track them during, and verify recovery after.